
Infection Risk in Cosmetic Surgery Tourism: What the Evidence Shows and How Korea Compares

Almost everything the evidence says about infection risk abroad points back at the facility, not the country. Photo: Cesar Badilla Miranda / Unsplash
Quick answer Infection is the most frequently reported complication in patients who travel abroad for cosmetic surgery, according to both a 2023 systematic review of 44 studies and the American Society of Plastic Surgeons' own briefing paper [1][4]. That finding describes the shape of reported harm, not a rate. The published literature is built almost entirely from patients who already had complications, so it has no denominator and cannot give you a percentage risk for any particular clinic. What it can do is tell you where to look: at facility accreditation, at who actually operates, at implant and device provenance, and at who will examine your wound in week two once you have flown home.
In this guide
What 'infection risk' actually means in this literature
Two independent bodies of evidence point the same way. Alkaelani and colleagues' PRISMA systematic review of aesthetic procedures performed abroad, covering 44 studies and 589 patients who presented with complications, found infection to be the most commonly reported complication [1]. The ASPS briefing paper on cosmetic surgery tourism states the same conclusion in plain terms: infections are the most common complication seen in patients who go abroad for cosmetic surgery [4].
It is worth being precise about what that claim is. It is a statement about the composition of reported harm - of the problems that get written up, infection is the largest single category - and not a statement that travelling abroad carries a measured infection rate of any particular size. ASPS lists unsightly scarring, haematoma and unsatisfactory results alongside infection as recurring complications [4]; infection simply dominates the published case material.
Why case series cannot give you a percentage
Both of the major reviews in this area are built from case reports and case series of patients who already had a problem. Alkaelani's 589 patients are 589 people who presented with complications [1]; Gilardi's 370 are 370 people who developed infections [2]. Neither study knows how many patients travelled and were fine, which means neither can produce a rate, a relative risk or an odds ratio. This is the single most important thing to understand before reading any headline about medical tourism infection rates.
Which organisms appear, and why mycobacteria matter
Alkaelani and colleagues report that most causative organisms in their pooled cases were bacterial, with a substantial share belonging to the Mycobacterium genus [1]. That detail is not trivia. Rapidly growing non-tuberculous mycobacteria behave unlike the ordinary staphylococcal wound infection a general practitioner sees weekly: onset can be delayed by weeks, the presentation can be indolent, and the organisms do not respond to the first-line antibiotics a clinician would reasonably reach for.
The downstream consequence is a diagnostic delay, and it is the single most avoidable harm in this whole picture. A patient who presents at home three weeks after surgery abroad with a low-grade, slowly worsening wound problem may be treated empirically for a common pathogen, improve marginally, and lose weeks before anyone cultures for mycobacteria. Telling the treating doctor, unprompted, that you had surgery abroad and when is what shortens that path.
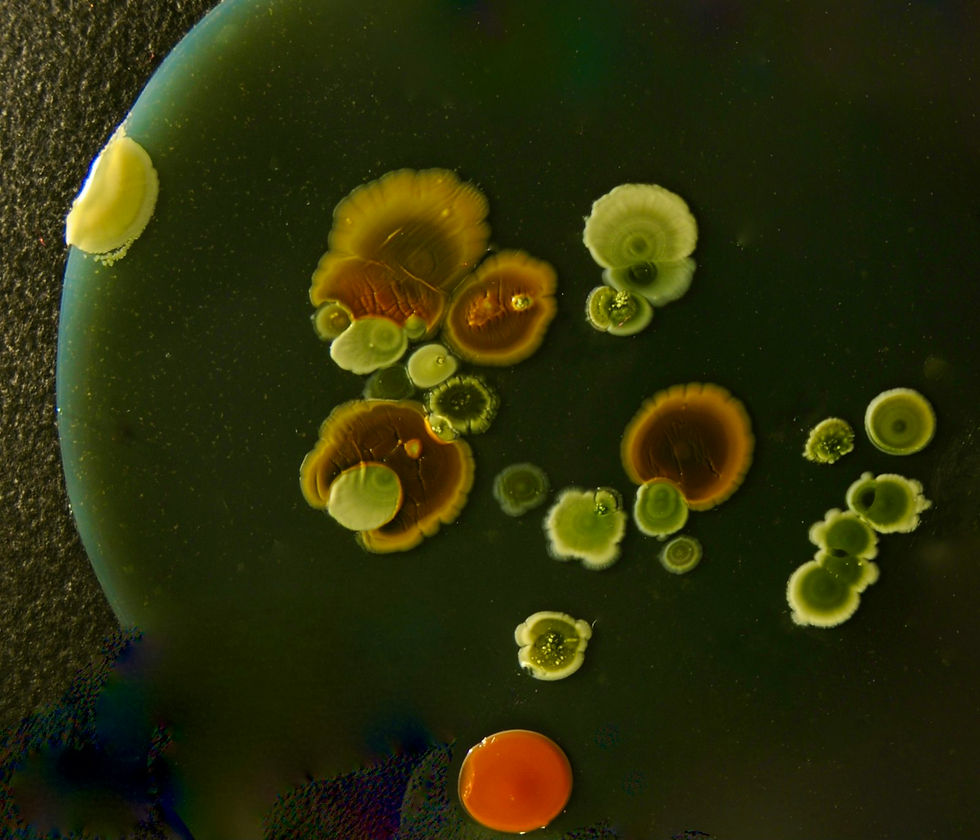
Mycobacteria grow slowly and need to be looked for deliberately - which is why telling your doctor you had surgery abroad changes the outcome. Photo: Guy Grandjean / Unsplash
What the reviews found | Reported pattern | What it should change in your planning |
Most common complication | Infection, across both the 44-study review and the ASPS briefing paper [1][4] | Make sterility and implant provenance your first questions, not your last |
Organism mix | Mostly bacterial, with a notable share from the Mycobacterium genus [1] | Disclose surgery abroad to any doctor who treats you, so cultures are taken |
Procedure most often linked to infection | Abdominoplasty [2] | Larger body-contouring cases deserve more scrutiny than small facial work |
Procedure linked to the most severe cases | Gluteal augmentation [2] | Severity, not just incidence, should inform whether to travel for it at all |
Most reported destination in the literature | Dominican Republic, in a US-dominated evidence base [2] | Read as research geography, not a destination safety ranking |
Follow-up provision | Limited or absent once the patient returns home [4] | Arrange a named local clinician before you fly out |
Revision outcomes | More complicated than the first operation, with less predictable results [4] | Budget a reserve and prefer avoiding revision over pricing it |
Why the facility matters more than the country
Gilardi and colleagues' procedure breakdown is the most actionable finding in the literature: abdominoplasty was the procedure most often linked to infection, and gluteal augmentation was associated with the most severe cases [2]. Both are large-surface, long-duration operations with substantial dead space - the conditions under which contamination becomes clinically significant. Neither finding is about a country. Both are about the operation and the environment it happens in.
ASPS frames the same issue institutionally. Its briefing paper warns that some destinations lack formal accreditation boards for physicians or facilities, that many facilities are privately owned in ways that make verifying the credentials of surgeons, anaesthesiologists and other staff difficult, and that devices and implants used abroad may not have been tested or approved by the patient's home regulator [4]. ASPS also states that its member surgeons operate only in accredited facilities [4], which is a useful shape for a question even outside the United States.
What you can actually verify about a Korean clinic
Start with the legal layer, because it is public. Korea requires medical institutions that recruit foreign patients to register for that activity, and registry data is published through the national open-data portal; the Gyeongju City dataset, listing registered institutions by name and street address and last updated in June 2026, is one worked example [5]. A facility that is courting international patients and cannot be found in the relevant registry is a question you should resolve before any money moves. The same applies to intermediaries - see how to check whether a Korean medical tourism agency is legally registered.
Then the clinical layer. Ask for the operating surgeon by name and confirm their specialty board certification rather than accepting 'our doctors are specialists'; the consulting doctor and the operating doctor are not always the same person, as who performs your surgery in Korea sets out. Ask who provides anaesthesia and what their qualification is. Ask what the facility's documented plan is for an intraoperative emergency and where the receiving hospital is - how Korean clinics handle medical emergencies describes what a credible answer contains.
The disclosure that shortens a diagnosis If you develop any wound problem after returning home, tell the treating clinician three things without being asked: that you had surgery abroad, the exact date, and what procedure was performed. Bring the operative note, the anaesthesia record and the implant identifiers with lot numbers. ASPS notes that local doctors may not know which technique the original surgeon used, which makes treatment harder [4]. Ask explicitly whether cultures should include atypical and slow-growing organisms. A notable share of reported organisms in travelled patients belong to the Mycobacterium genus, which does not respond to routine first-line antibiotics [1]. Do not wait for a photo review from overseas before being examined in person. Spreading redness, fever, increasing pain, discharge or wound separation warrant same-day local assessment. |
If an infection starts after you fly home
ASPS is blunt about the structural problem: cosmetic surgery tourism packages provide limited follow-up care if any once the patient has returned, patients may struggle to find a qualified surgeon willing to treat a complication or perform a revision, and local doctors may not know what technique was used [4]. Every one of those obstacles is cheap to remove before departure and expensive to remove while you are febrile.
The pre-emptive version takes an afternoon. Collect the full record set before you leave the clinic - clinical records to request before you leave a Korean clinic is the checklist. Identify a named clinician at home who has agreed to review the wound in week two and has seen those records. Establish the clinic's escalation route: who answers, in which language, in what hours, and what their threshold is for sending you to a local emergency department rather than waiting. Our guide to remote follow-up after returning home covers how to run that handover.
How to read any infection statistic you are quoted
Three questions defuse almost every misleading figure in this field. First, what is the denominator? If the number comes from a review of patients who already had complications, there is no denominator and therefore no rate [1][2]. Second, where did the patients come from? A US-dominated evidence base describes US travel patterns, which is why the Dominican Republic appears as the leading destination in Gilardi's dataset [2] rather than anywhere in East Asia. Third, which procedure? The reported burden differs sharply between abdominoplasty, gluteal augmentation and a small facial procedure [2].
What the research says
44 studies, 589 patients: infection leads, and mycobacteria recur
Alkaelani and colleagues performed a PRISMA-guided systematic review of complications after aesthetic procedures performed abroad, pooling 44 studies and 589 patients who presented with complications. Infection was the most common complication, most causative organisms were bacterial, and a substantial share belonged to the Mycobacterium genus. The authors call on regulators to educate the public so patients can make informed choices [1].
The limitation is intrinsic to the design: a pooled series of complicated cases has no denominator, so it cannot produce an incidence rate, and publication patterns determine which cases appear. What it does deliver is a reliable map of mechanism. For a patient, the actionable reading is that infection control and implant provenance are the right questions to press on, and that mycobacterial involvement makes early disclosure to a home-country doctor genuinely consequential.
36 articles, 370 infections, severity graded by procedure
Gilardi and colleagues reviewed 36 articles covering 370 patients with infections following cosmetic surgery abroad, grading severity using the Clavien-Dindo classification. Most reports came from the United States and the Dominican Republic was the most common destination. Within the procedure mix, abdominoplasty was most often linked to infection and gluteal augmentation was associated with the most severe cases [2].
Its limitations are the same family: a US-skewed, case-report-derived sample whose geography reflects research and referral patterns rather than destination risk. The meaning for a reader is nonetheless specific and transferable. Severity scales with the invasiveness of the operation and the size of the surgical field, which is a property of the procedure and the facility rather than of the country - so the decision that most changes your exposure is which operation you choose and where it is performed, not which passport stamp you collect.
A travel medicine review on what is still not being measured
Pereira and colleagues' review in the Journal of Travel Medicine examines the scale and economics of cosmetic surgery tourism and the complication profile of procedures performed abroad, concluding that travel medicine literature gives little attention to non-surgical morbidity in these travellers and recommending original research on patient motivations together with pre-travel psychological counselling [3]. As a narrative review it generates direction rather than effect sizes.
For the reader, this is the paper that explains why nobody can honestly quote you a risk percentage: the primary studies that would produce one have not been done. It also identifies the part of preparation that is systematically skipped - the structured conversation about motivation and expectation before a non-refundable decision - which costs nothing and is the only intervention in this literature that is unambiguously available to you.
Frequently asked questions
Is infection genuinely the most common problem after cosmetic surgery abroad?
It is the most commonly reported complication in both a 2023 systematic review of 44 studies and the ASPS briefing paper on cosmetic surgery tourism [1][4]. That describes the composition of reported harm rather than a measured rate - the published literature is drawn from patients who already had complications and has no denominator.
Does the research show Korea is riskier or safer than other destinations?
Neither. The destination distribution in this literature reflects where the studied patients travelled and where their complications were written up - most reports are from the United States, with the Dominican Republic as the leading destination [2]. It is not a safety ranking, and it says nothing specific about Korea.
Why does it matter that mycobacteria show up in these cases?
A substantial share of causative organisms in pooled travelled-patient cases belong to the Mycobacterium genus [1]. These can present late and indolently and do not respond to routine first-line antibiotics, so a doctor who does not know you had surgery abroad may treat the wrong organism for weeks. Disclose it unprompted.
Which procedures deserve the most caution?
In the reviewed literature, abdominoplasty was the procedure most often linked to infection and gluteal augmentation was associated with the most severe cases [2]. Larger, longer operations with bigger surgical fields carry a heavier reported burden than small facial procedures.
What should I ask a clinic specifically about infection control?
Ask who operates and their board certification, who provides anaesthesia, how instruments are reprocessed and sterilised, and for the implant or device name, manufacturer, Korean regulatory approval status and the lot number in your file. A clinic that answers in writing is behaving differently from one that deflects.
References
Alkaelani MT, et al. Complications of Medical Tourism in Aesthetic Surgery: A Systematic Review. Annals of Plastic Surgery, 2023. PMID 37962261; DOI 10.1097/SAP.0000000000003683.
Gilardi R, et al. Infective complications of cosmetic tourism: A systematic literature review. Journal of Plastic, Reconstructive & Aesthetic Surgery, 2023. PMID 37320953; DOI 10.1016/j.bjps.2023.05.021.
Pereira RT, et al. Aesthetic journeys: a review of cosmetic surgery tourism. Journal of Travel Medicine, 2018. PMID 29924349; DOI 10.1093/jtm/tay042.
American Society of Plastic Surgeons. Briefing Paper: Cosmetic Surgery Tourism. ASPS. Reviewed 13 October 2026.
Public Data Portal of Korea. Medical institutions registered to attract foreign patients (open dataset). data.go.kr, provided by Gyeongju City, Gyeongsangbuk-do; record updated 14 June 2026.
International Society of Aesthetic Plastic Surgery. ISAPS Global Survey on Aesthetic/Cosmetic Procedures. ISAPS. 16th Global Survey, covering procedures performed in 2025, closed and under analysis; annual reports from 2010 onward published.
Related reading
Warning Signs of Complications After Cosmetic Surgery: When to Call Your Clinic
Korean Clinic Credentials: Board Certification, KSPRS Membership and Hospital Tiers
Who Performs Your Surgery in Korea: Verifying the Operating Surgeon Before You Consent
Clinical Records to Request Before You Leave a Korean Clinic
How Korean Clinics Handle Medical Emergencies During Cosmetic Surgery
About this guide: Korean Plastic Surgery Info is an independent editorial resource for international patients researching cosmetic and reconstructive care in South Korea. We do not own, operate or represent any clinic, and we receive no commission, referral fee or booking fee from any hospital mentioned on this site. This article is general information, not medical advice, and it cannot substitute for an in-person assessment by a licensed physician who has examined you. Last reviewed 13 October 2026.


Comments